Tag: hipaa

  • Healthcare Mobile App Development: A Complete 2026 Guide

    Healthcare Mobile App Development: A Complete 2026 Guide

    Healthcare mobile app development is the process of building iOS or Android apps that handle patient or clinical data, which means HIPAA compliance, strong security, and often EHR integration are part of the job from day one, not features you bolt on later. A basic HIPAA-ready MVP typically starts around $60,000 and ships in about four to six months. The cost and timeline track compliance, the integrations you need, and whether your app is a wellness tool or a regulated medical device.

    Most healthcare apps do not fail because the idea was wrong. They fail because the team treated a medical app like a regular app, and then hit compliance, security, and integration walls halfway through the build. By then the budget is spent and the timeline is gone.

    This guide is written to keep you out of that hole. It covers what healthcare mobile app development actually involves in 2026, what it costs, how long it takes, where HIPAA and the FDA fit in, and how to choose a team that has shipped this kind of app before. We have built and shipped mobile health products since 2016, including medical translation and nutrition platforms where a wrong answer carries real consequences, so the advice here is what we would tell a founder over a call.

    Key takeaways

    • Healthcare app development means compliance and security are part of the build from day one, not add-ons.
    • Know early whether your app is a wellness product or an FDA-regulated medical device. The line is narrower than most founders expect.
    • HIPAA in practice means AES-256 at rest, TLS 1.2 or higher in transit, MFA, audit logs, and signed BAAs with every vendor.
    • A HIPAA-ready MVP starts around $60,000 and ships in four to six months. EHR integration adds the most to both cost and timeline.
    • Choose a team with shipped healthcare apps, compliance fluency, named senior engineers, and clear code ownership.

    What healthcare mobile app development actually means

    A healthcare app is any mobile app that touches health data or clinical workflows. That covers a lot of ground: a patient booking a telehealth visit, a nurse checking a chart at the bedside, someone logging blood sugar, a therapist running a session. What ties them together is the data. The moment your app stores, moves, or displays information that can identify a person and their health, you are in regulated territory, and the rules shape every decision after that.

    This is the part founders underestimate. In a normal app, security and privacy are good practice. In a healthcare app, they are the product. Encryption, access control, audit logs, and consent are not features you add if there is time. They are the foundation the rest of the app sits on.

    Health app vs medical app: the line that changes everything

    Not every health app is a medical device, and the difference decides how heavy your build is. A wellness app that tracks steps, logs meals, or reminds you to take medication is usually a general wellness product with a lighter regulatory load. An app that diagnoses, treats, or drives a clinical decision can be a medical device that the FDA regulates as Software as a Medical Device (SaMD).

    The FDA draws the line at intended use. A blood pressure app that just displays your readings usually sits in enforcement discretion. Add a feature that interprets those readings and says you may have hypertension and should ask about medication, and you have crossed into regulated territory.

    That distinction is set out in the FDA’s guidance on device software functions and mobile medical applications. Check the current version before you finalise your feature list, because the boundary has moved more than once and it moves in the direction of more scrutiny, not less. Decide which side you are on before you build. It changes your timeline, your budget, and your legal exposure.

    HIPAA compliance: what it really requires

    If your app handles protected health information for anyone in the US, HIPAA applies. It is not a certificate you buy or a checkbox at the end. It is a set of safeguards baked into how the app is built, hosted, and run. Here is what that means in practice.

    • Encryption everywhere. Protected health information must be encrypted at rest and in transit. The working standard is AES-256 for stored data and TLS 1.2 or higher for data moving across the network.
    • Strong access control. Every user gets the minimum access they need, with multi-factor authentication, automatic screen lock, and session timeouts. On mobile specifically, that includes blocking screenshots on iOS and screen recording on Android so health data does not leak out the side door.
    • Audit logging. The system records who accessed what and when, so a breach can be investigated and access can be proven.
    • A Business Associate Agreement (BAA). Every vendor that touches the data, your cloud host, your video provider, your analytics, must sign a BAA. Using a service that will not sign one is a compliance gap by itself.
    • Risk assessments and breach response. HIPAA expects regular security risk assessments and a real plan for breach notification.
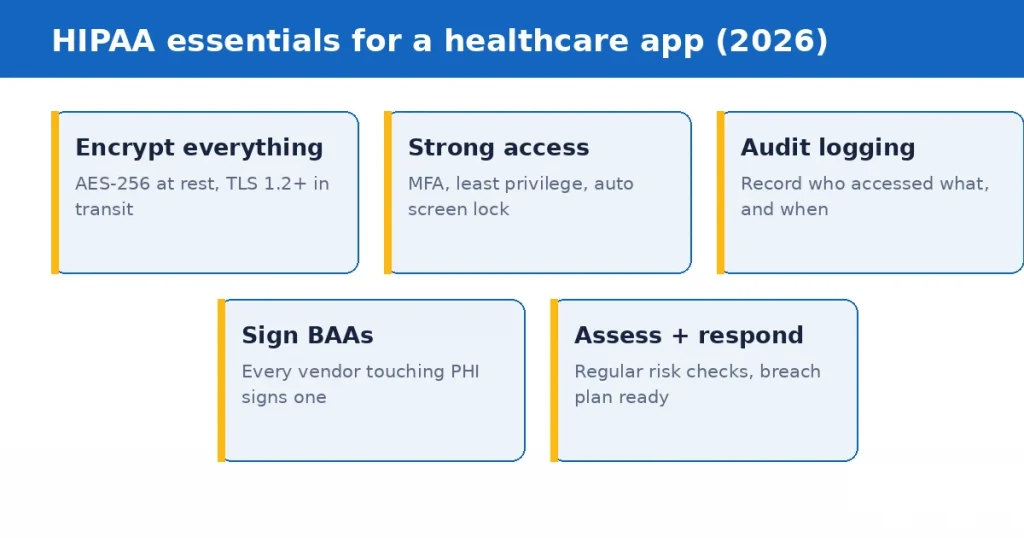
    Five HIPAA essentials for a healthcare app: encryption, access control, audit logging, business associate agreements, and risk assessment

    The Security Rule has been under active revision, and the direction of travel is toward making encryption and multi-factor authentication mandatory rather than addressable, with tighter breach timelines. Build to the stricter bar now. It is cheaper than retrofitting when a rule finalises, and none of it is wasted work even if the timeline slips.

    Founder note

    HIPAA compliance is not the whole app, it is a property of the app. It adds meaningfully to the base build cost, but retrofitting it into a non-compliant app later costs far more and sometimes means rebuilding. Start compliant.

    iOS vs Android: which platform first

    You do not have to pick one forever, but for an MVP, building one platform well beats building two platforms poorly. The right first choice depends on who your users are.

    If your users are patients in the US, iOS often makes sense first, since iPhone holds a large share of the US consumer market and Apple’s health frameworks are mature. If your app is for clinicians or serves a broad or global population, Android may matter more because of device range. If your budget is tight and you want both from day one, cross-platform is the practical answer, which brings us to the next decision.

    Native or cross-platform

    Cross-platform frameworks like Flutter and React Native let you build one codebase for both iOS and Android, which lowers cost and speeds up delivery. For most healthcare apps, that is the right call.

    You reach for native when you need heavy device-specific performance, deep integration with Apple HealthKit or Google Health Connect, or tight control over hardware like Bluetooth medical devices. Continuous glucose monitors, connected inhalers, and anything with a real-time data stream from a device tend to push you native, or at least native for that one module.

    A good team helps you decide based on your product, not on what they prefer to build. If a team recommends the same stack for every client regardless of the brief, that tells you something.

    We work across Flutter app development and React Native app development as well as native iOS and Android, and the choice genuinely changes per project.

    Core features of a healthcare app

    The exact feature set depends on whether your app is patient-facing, provider-facing, or both. These are the building blocks most healthcare apps draw from.

    • Secure sign-in and identity: MFA, biometric login, role-based access.
    • Patient profiles and health records, with consent controls.
    • Appointment booking and reminders.
    • Telehealth: encrypted video, chat, and file sharing.
    • Tracking and monitoring: medication, symptoms, vitals, often synced from wearables.
    • Notifications that respect privacy, with no health details on a lock screen.
    • EHR integration, so the app talks to the systems clinicians already use.

    The trap is trying to ship all of this at once. The apps that succeed launch with the two or three features that solve the core problem, prove people use them, and add the rest based on real feedback.

    What to cut from version one

    This is the conversation we have with almost every healthcare founder, and it saves more money than any other decision in the project.

    Cut multi-role from the first release. Building for patients and clinicians and administrators at once triples your permission model, your testing surface, and your compliance review. Pick the role that proves the product and build only for them.

    Cut EHR integration if you can prove value without it. It is the single biggest cost and schedule driver. Plenty of products validate with manual data entry or a simple export first, then integrate once a health system has actually committed.

    Cut native wearable integration. Apple HealthKit and Google Health Connect sound cheap because the SDKs are free. The cost is in the edge cases: missing data, duplicate readings, timezone drift, and users who revoke permission halfway through a study. Add it when the core loop works.

    Cut offline mode unless clinicians in the field are your users. Offline-first is a genuine engineering commitment involving conflict resolution and sync logic. It is worth it for a community health worker in a low-connectivity area. It is not worth it for an urban telehealth app.

    Do not cut audit logging, access control, or encryption. These are the things founders try to defer and they are the things you cannot add cleanly later. Every retrofit we have done started as a deferral.

    The pattern across the healthcare products we have shipped is the same: the launch feature set is smaller than the founder first imagined, and the compliance foundation is deeper. That combination ships. The reverse does not.

    EHR integration: the part that quietly drives cost

    If your app needs to read or write clinical data, it has to connect to electronic health record systems like Epic or Cerner. This is where a lot of healthcare budgets get their surprise.

    Modern EHRs expose FHIR-compliant APIs, the current healthcare data standard, which makes standard integrations relatively clean. Older systems that rely on HL7 v2 messaging or custom interface engines are a heavier lift.

    Three things drive the difference in effort:

    Which standard the system speaks. A FHIR API with good documentation is a different project from an HL7 v2 feed arriving over a legacy interface engine.

    Read or write. Reading patient data is far simpler than writing back into a clinical record. Write-back triggers a much heavier review process on the health system’s side, and their timeline is not yours to control.

    Whose sandbox you get. Some health systems have a working developer sandbox and a defined app review process. Others have a committee and a six-week wait for a call. This is often the real schedule risk and it has nothing to do with your code.

    If EHR integration is in your plan, scope it early and start the conversation with the health system before you start building. Budget and schedule both move more on this than on almost anything else.

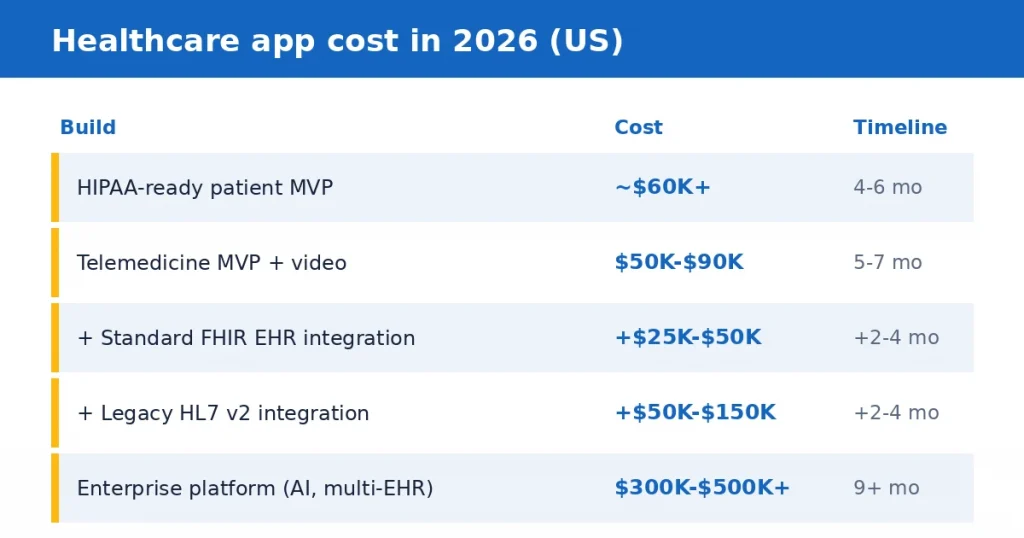
    How much does healthcare app development cost in 2026

    There is no single price, because a wellness tracker and a telemedicine platform with EHR write-back are completely different products. The ranges below reflect what we see when scoping healthcare builds for the US market. Treat them as a starting frame, not a quote. We scope your specific app before giving a real number.

    App typeTypical cost (US, 2026)Rough timeline
    HIPAA-ready patient MVPAround $60,000 and up4 to 6 months
    Telemedicine MVP (portals, encrypted video, booking)$50,000 to $90,0005 to 7 months
    Real-time video infrastructure (add-on)$15,000 to $40,000Included above
    Standard FHIR EHR integrationAdd $25,000 to $50,000Add 2 to 4 months
    Legacy HL7 v2 integrationAdd $50,000 to $150,000Add 2 to 4 months
    Enterprise platform (AI, multi-EHR, multi-platform)$300,000 to $500,000 and up9 months and up
    Healthcare app development cost and timeline ranges in 2026, from a HIPAA-ready MVP at around 60,000 dollars to an enterprise platform above 300,000 dollars

    Compliance work is not a line item you can remove. It runs through security engineering, documentation, audit logging, vendor agreements, and testing, and it is a meaningful share of any healthcare build.

    Why healthcare apps cost more than regular apps

    The extra cost is not padding. It buys encryption and security engineering, compliance work and documentation, audit logging, signed vendor agreements, careful testing against real clinical workflows, and integrations that have to be exact because a wrong record is a patient safety issue.

    A consumer photo app can ship a bug and patch it Tuesday. A medication app cannot.

    How long does it take

    A focused HIPAA-ready MVP usually ships in about four to six months. Add telehealth video and you are closer to five to seven. Add EHR integration and you add two to four months on top.

    The timeline is driven less by screen count and more by compliance, integrations, and testing. There is also a category of delay that is not yours to control: health system review cycles, app store review for medical claims, and legal sign-off on your privacy policy and consent flows. Build slack for those into the plan rather than discovering them in month five.

    How to choose a healthcare app development company

    This is a specialist build, and general app teams get healthcare wrong in expensive ways. Here is how to tell a team that has shipped medical apps from one that will learn on your budget.

    • Shipped healthcare work. Ask for live health apps they have built, ideally in your space. Compliance experience shows up in the details they mention without being asked.
    • Compliance fluency. They should talk about HIPAA, BAAs, encryption, and the health app versus medical device line naturally, and tell you early if you are heading toward FDA territory.
    • Named senior engineers. You want senior people on your project, not a pitch team that hands the build to juniors. Ask who writes your code and whether you can interview them.
    • Clear ownership. In writing, you own the source code, the IP, and the app store listings, with no lock-in.
    • A real post-launch plan. Healthcare apps need ongoing maintenance, security patching, and OS updates. A team with no answer for month twelve is planning to disappear.

    Questions worth asking on the first call

    Five questions that separate teams quickly:

    1. Which of your healthcare apps is live right now, and can I download it?
    2. Who signs the BAA, you or the client, and which vendors in your usual stack will sign one?
    3. Based on what I have described, do you think this is a medical device? Why?
    4. What would you cut from my first version, and what would you refuse to cut?
    5. Who exactly writes the code, and can I speak to them before we sign?

    A team that has done this work answers all five without hedging. A team that has not will be vague on two or three, usually the medical device question and the one about who writes the code.

    Red flags to walk away from

    • A quote far below everyone else, which usually means compliance is missing from the scope.
    • Vague answers on HIPAA, or a promise that compliance is easy.
    • No named engineers and no shipped healthcare apps to show.
    • Fuzzy code-ownership terms.

    If you are weighing an in-house hire against an agency, our hire mobile developers page covers the engagement models, and the honest answer is that healthcare is one of the areas where prior domain experience matters more than raw headcount.

    How we approach healthcare apps at Mobilions

    We build healthcare apps compliant from the first commit, not compliant-later. That means encryption, access control, and audit logging in the foundation, signed BAAs with every vendor in the stack, and an honest early read on whether your app is a wellness product or heading toward SaMD. Senior engineers scope, build, and support the product, and you own the code, the IP, and the documentation throughout.

    We have shipped mobile health products since 2016. Careslate is a HIPAA-compliant AI medical translation app with live two-way audio built on a custom three-stage pipeline, used in clinical settings where a mistranslation has consequences. JoinBeet is a personalised medical nutrition platform with meal matching, wearable sync, and role-based admin access.

    Both are on our healthcare software development page alongside how we approach the sector, and the mobile side of that work sits under mobile app development.

    Ready to scope your healthcare app?

    Tell us what you want to build and who it is for. A senior engineer will give you an honest read on cost, timeline, and the compliance path, including the parts you can cut from the first version. Book a discovery call.

    Frequently asked questions

    How much does it cost to build a healthcare app?

    In the US in 2026, a HIPAA-ready patient MVP typically starts around $60,000, a telemedicine MVP runs $50,000 to $90,000, and enterprise platforms with AI and EHR integration reach $300,000 to $500,000 or more. The number tracks scope, integrations, and whether the app is regulated. Compliance work is a meaningful share of any healthcare build and cannot be removed from the scope.

    How long does it take to develop a healthcare app?

    A focused HIPAA-ready MVP usually ships in about four to six months. Telehealth video pushes that to five to seven months, and EHR integration adds another two to four months. Compliance and testing drive the timeline more than the number of screens, and health system review cycles can add delay you do not control.

    What is HIPAA compliance for a mobile app?

    It is a set of safeguards for protected health information: AES-256 encryption at rest, TLS 1.2 or higher in transit, multi-factor authentication, access controls, audit logging, and signed Business Associate Agreements with every vendor that touches the data. It is built into the app, not added at the end.

    Does my healthcare app need FDA approval?

    Only if it functions as a medical device, meaning it diagnoses, treats, or drives a clinical decision. Wellness trackers and appointment apps usually do not. Apps that interpret data and make clinical claims can be regulated as Software as a Medical Device. The line is narrow, so get an assessment early rather than after the build.

    What is the difference between a health app and a medical app?

    A health or wellness app tracks or supports general wellbeing, like steps, meals, or reminders, with a lighter regulatory load. A medical app diagnoses, treats, or informs a clinical decision and can be an FDA-regulated medical device. Intended use decides which one you are building, not the feature list on its own.

    Should I build for iOS or Android first?

    If your users are US patients, iOS is often a strong first choice. If you serve clinicians or a broad or global audience, Android may matter more. If you want both on a tight budget, a cross-platform build with Flutter or React Native is usually the practical answer.

    How much does HIPAA compliance add to the cost?

    It is not a separate line you can price and remove. Compliance runs through security engineering, audit logging, documentation, vendor agreements, and testing, so it raises the cost of the whole build rather than sitting beside it. Retrofitting compliance into an app built without it costs far more, so it is cheaper to start compliant.

    What is EHR integration and why does it cost so much?

    EHR integration connects your app to systems like Epic or Cerner so it can read or write clinical data. A modern FHIR integration commonly adds $25,000 to $50,000, while legacy HL7 v2 integration can add $50,000 to $150,000 and two to four months. Writing back into a clinical record is significantly harder than reading, and health system review timelines are not yours to control.

    Can I build a healthcare app without technical skills?

    Yes, most healthcare app founders are not engineers. You bring the clinical or business insight and partner with a team that handles the build and compliance. What matters is choosing a team that has shipped healthcare apps and can guide you through HIPAA and the medical device question.

    What features should my healthcare app include?

    Start with secure sign-in, patient profiles with consent, and the two or three features that solve your core problem, whether that is booking, telehealth video, or tracking. Add EHR integration, wearables, and extra features later based on real user feedback, not all at once.

    How do I make sure my healthcare app is secure?

    Encrypt data at rest and in transit, enforce MFA and least-privilege access, log every access, block screenshots and screen recording of health data, sign BAAs with all vendors, run regular security risk assessments, and test against real clinical workflows before launch.

    Does Mobilions build healthcare apps?

    Yes. We build HIPAA-compliant iOS, Android, and cross-platform healthcare apps, and have shipped mobile health products since 2016, including a medical translation app for clinical settings and a nutrition platform with wearable sync. We build compliant from day one and hand you full ownership of the code and IP.



  • Healthtech MVP Development: How to Build a Compliant MVP Without Overbuilding

    Healthtech MVP Development: How to Build a Compliant MVP Without Overbuilding

    Most healthtech startups do not die from a bad idea. They die from a good idea built too big. The founder raises a seed round, spends nine months and most of the money building a full platform, and runs out of runway before a single clinician or patient has used the thing for real. Healthtech startup MVP development is the fix for that pattern. It is the discipline of building the smallest honest version that proves your idea works and keeps patient data safe, and nothing more, until the market tells you what to build next. Done well, healthtech MVP development is less about writing code and more about restraint.

    The safe part is what makes healthcare different. In most industries you can ship fast, cut a few corners on security, and tidy up later. In healthcare the corner you cut is someone’s medical record, and the rules do not care that you are small. A data breach during your MVP carries the same legal weight as one at a company with millions of users. So the goal is not only to build less. It is to build less while getting the few things that matter exactly right.

    We have built medical software since 2016, including JoinBeet, a nutrition platform that syncs with wearables, and Careslate, a translation tool used in clinical settings. This guide is the long version of the advice we give founders on the first call: what an MVP really is, what compliance actually costs you, how to decide what to cut, and the specific mistakes that quietly drain a seed round.

    Key takeaways

    • An MVP is the smallest compliant version that proves one core loop. If your description has several “ands,” you are describing a full product, not an MVP.
    • In the US, a healthcare MVP from an experienced team usually runs $100,000 to $400,000, and HIPAA work adds roughly 40 to 80 percent over a comparable consumer app.
    • Most properly scoped healthcare MVPs take three to six months. A quote of a few weeks almost always means compliance was left out of the plan.
    • Build compliance in from sprint one: encryption, role-based access, multi-factor login, audit logs, and a signed BAA with every vendor that touches patient data. Retrofitting later costs three to five times more.
    • Cut everything that is not the core loop, validate with real clinicians before building, and keep full ownership of your code and IP.

    MVP, prototype, or full product? Know what you are building

    These three words get used as if they mean the same thing, and the confusion is expensive. A prototype is a clickable mockup. It shows how the app looks and moves, has no real backend, and stores no real data. You build it in days to test an idea with users, not to launch. An MVP is a working product with the single core feature that delivers value, built properly enough to put in front of real patients or providers, with real compliance behind it. A full product is the whole vision: the roadmap, the integrations, the polish, the second and third user types.

    Founders who ask for an MVP but describe a full product are the ones who blow the budget, and it happens on almost every first call. Here is the quick test we use out loud: read your feature list back. If it has more than one “and” in it, you are probably describing a full product. “Patients log symptoms and providers review them” is an MVP. “Patients log symptoms and providers review them and there is a billing module and a pharmacy integration and a family portal” is a two-year platform wearing an MVP costume.

    The reason this matters so much in healthcare is that every extra feature is not just extra build time. It is extra data, extra access paths, extra compliance surface, and extra ways to leak something you should not. In consumer software, scope creep costs money. In healthtech, it costs money and risk.

    Why healthcare MVPs cost more than regular apps

    Take any app idea, add the words “for patients,” and the price roughly doubles. The real cost of healthtech MVP development is not agencies padding the invoice. It is where the work actually goes.

    • Compliance is architecture, not a feature. HIPAA shapes how you store data, who can see it, how it moves, and how long you keep the logs. These are foundational decisions. Change them after launch and you are rebuilding the plumbing with the water still running.
    • Security has to be real, not theater. Encryption at rest and in transit, multi-factor login, role-based access, tamper-proof audit trails. On a to-do app these are nice to have. On a health app they are the product, and reviewers will check.
    • You need clinical input. A clinician has to tell you what is safe, what is a liability, and what workflow a nurse will actually tolerate on a night shift. That review time is real, skilled work, and it is not optional.
    • Formal QA and documentation. Healthcare software carries a paper trail: what you tested, what you decided, why. That rigor protects you, and it takes time.

    Industry guides put a US healthcare MVP from an experienced agency somewhere between $100,000 and $400,000, with the HIPAA work adding roughly 40 to 80 percent over the same app without it. Treat those as ranges, not a quote. The honest number for your product comes after someone scopes it, because a symptom tracker and a remote patient monitoring platform are not the same job. The one figure to burn into memory: retrofitting compliance after launch runs three to five times more than building it in from the start. Anyone quoting you six weeks and a bargain price has either not understood the compliance load or is planning to hand you the bill for it later.

    How much does a healthcare MVP actually cost?

    Cost is the first question almost every founder asks, so let us break the range down instead of hiding behind “it depends.” The cost of healthtech MVP development is driven by four things: how much protected health information you touch, how many integrations you need, how many user types you support at launch, and how senior the team is.

    At the lower end, near $100,000, you have a single user type, one core loop, minimal integrations, and a team that has done this before so they are not learning HIPAA on your dime. In the middle you add real integrations, a second workflow, and more clinical validation. At the top, past $300,000, you are usually looking at device data, third-party medical systems, or a product that edges toward being regulated as a medical device, which changes everything.

    Watch the costs nobody warns you about. Compliance counsel to confirm what rules apply. Security review or a light penetration test before launch. BAA-eligible hosting, which costs more than a standard cloud plan. Ongoing maintenance, which for any live health product runs meaningfully higher than a consumer app because you cannot let dependencies or security patches drift. Budget for the year, not just the build, or you will ship the MVP and then discover you cannot afford to keep it alive.

    How long does it take to build a healthcare MVP?

    Three to six months is the honest range for healthtech MVP development that is properly scoped. The spread depends on the same things that drive cost: compliance depth, integrations, and how disciplined you are about scope.

    A rough shape of those months: a couple of weeks on scoping, architecture, and confirming which rules apply, so you are not designing blind. Then the build in short cycles, with the compliance foundations going in first, not last. Then testing, including on real devices and against the security requirements, not just a simulator. Then a careful launch. The teams that hit the short end of that range are the ones that cut scope hard and had a clinician in the room early. The teams that blow past six months are almost always the ones who kept saying “while we are at it, let us also add.”

    HIPAA and FDA: what compliance really means for your MVP

    This is the section founders skim and then regret skimming. Two different rulebooks can apply to a health app, and they answer different questions.

    HIPAA is about protecting health data. It kicks in the moment your app stores, processes, or transmits protected health information, which is basically identifiable health data. Telemedicine apps, patient monitoring, anything tied to a clinic or a diagnosis: HIPAA applies. If your app genuinely never touches protected health information, a pure wellness tracker with no identifiable medical data, your obligations are much lighter. The trap is assuming you are in the light category when you are not, so get a straight answer early, ideally from someone who has shipped in healthcare before. The US Department of Health and Human Services publishes the actual rules at hhs.gov/hipaa.

    For an MVP, being HIPAA compliant does not mean a full enterprise security program. It means the foundations are right from sprint one: data encrypted at rest and in transit, role-based access so people see only what they should, multi-factor login, a tamper-proof audit log of who touched what, and a signed Business Associate Agreement with every vendor that handles patient data on your behalf.

    That last one matters more than founders expect. Missing BAAs are the single most common compliance failure in audited cases, and they are the easiest thing to forget when you are wiring up a third-party service at 11pm.

    FDA is a separate question, and it is about risk, not data. Your app may be regulated as a medical device if it is meant to diagnose, treat, cure, or prevent disease, or to affect the structure or function of the body. A symptom logger that helps a patient track how they feel is usually fine. An app that reads sensor data and tells someone they are having a cardiac event is a different animal.

    The FDA classifies devices into three risk classes and, for many low-risk apps, intends to exercise enforcement discretion, meaning it will not enforce the full requirements. Higher-risk functions can need a 510(k) clearance or, at the top, premarket approval. The FDA lays out which software functions it regulates at fda.gov.

    None of this is legal advice, and that is the point: before you build, get a short read from someone who knows this area, because the answer changes your architecture, your timeline, and your budget.

    The data security your MVP needs on day one

    Strip the jargon and this is a short, concrete list. Encrypt data at rest and in transit, using current standards. Put every account behind multi-factor login. Give people the least access they need to do their job, and nothing more. Log every access to patient data in a way nobody can quietly edit. Sign a BAA with any service that stores or processes that data. Host on infrastructure that supports all of the above, which usually means a plan built for regulated workloads rather than the cheapest tier.

    You do not need a 40-page security policy to launch an MVP. You do need these six things done properly, because they are exactly the ones that are painful and expensive to add once real patient data is already in the system.

    Deciding what to cut is the hardest, most valuable skill

    An MVP is defined by what you leave out, and cutting is harder than building because everything on the list feels important to the person who wrote it. Here is the method that works. Take your feature list and sort every single item into two piles: “the product does not work without this” and “everything else.” The first pile is your MVP. The second pile is your roadmap. There is no third pile.

    For most healthtech MVPs the core is a single loop. A patient logs symptoms and a provider reviews them. A user scans a label and gets a result. A caregiver records a reading and the system flags it. Build that one loop end to end, properly and compliantly, and stop. Cut the dashboard with twelve chart types. Cut the social feed, the gamification, the second user role, the third language, the admin panel you will not need until you have a hundred users. None of those are wrong. They are just not first.

    When we built JoinBeet, this was the whole discipline: get the core nutrition and tracking loop working with wearable sync before adding anything else. It is not glamorous, and founders often push back because the cut features are the ones they pitched to investors. But scope discipline is the single habit that saves the most money and time in healthtech MVP development, and it is the one most first-time founders skip.

    Validate before you build, not after

    You can test a healthcare idea without writing the app, and you should. Show ten target clinicians or patients the prototype and ask one blunt question: what would stop you using this? In healthcare the blocker is rarely the feature you are worried about. It is trust, workflow fit, liability, or the simple fact that a busy clinician will not add a step to their day for a maybe. You want to hear that before you spend the money, not after the launch party.

    This is also the part non-technical founders can own completely, and it is where they add the most value. You do not need to code to validate an idea, recruit clinicians, run interviews, and lead the product. You need to ask sharp questions and sit with the awkward answers instead of arguing with them. The founders who do this well walk into the build already knowing what the first version has to do, which is why their MVPs cost less and land better.

    Build vs buy, and who should build it

    Two decisions hide inside “how do I get this built.” The first is build versus buy. Build the part that is your actual product, the thing that makes you different and that you would be embarrassed to outsource. Rent everything else. Authentication, hosting, payments, even large parts of the compliance tooling are solved problems with mature vendors behind them. Writing your own version of any of them is a way to spend your runway on work no user will ever thank you for.

    The second decision is who builds it: in-house, an agency, or freelancers. An in-house team is the right answer when you have the funding and a technical co-founder who can lead it, because you are hiring for the long haul.

    Freelancers can be fine for a narrow piece of work, but stitching a compliant health product together from several independent contractors, none of whom owns the whole picture, is how compliance gaps appear. For most early healthtech startups, a senior team that has shipped compliant health software before will get you to a safe launch faster, because they have already made the expensive mistakes on someone else’s project. Whichever route you take, insist on senior people with real healthcare experience, and make ownership non-negotiable: the source code, the IP, and the documentation are yours.

    How to choose an MVP development company (and the red flags)

    If you go the agency route, the choice matters more in healthcare than anywhere else, because the cost of picking wrong is not just a bad app, it is a compliance liability with your name on it. Ask the questions that actually separate teams.

    • Have you built HIPAA-compliant software before, and can you talk me through how you handled encryption, access control, and BAAs?
    • Who owns the code and IP when we are done? (The only acceptable answer is “you do.”)
    • Who will actually be on my project, and how senior are they?
    • How do you decide what goes in the MVP versus the roadmap?
    • What happens after launch, and what does support cost?

    The red flags are just as telling. A team that treats compliance as your problem to sort out separately. A quote that is dramatically cheaper than everyone else, which usually means the compliance work is missing from the scope. Vague answers about who owns the code. No named senior engineer, just a promise of “our team.” And anyone who agrees to your full feature list on the first call without pushing back on scope has told you they will build whatever you say, right up until the money runs out.

    Protecting your idea and your IP

    Founders worry about someone stealing the idea, and while the idea is rarely the valuable part, the concern points at something real: ownership. Use a straightforward NDA with any team you talk to in depth. More importantly, make sure your contract states plainly that you own the source code, the intellectual property, and the documentation, with no lingering license back to the agency and no dependency that traps you. The nightmare is not a competitor copying your concept. It is discovering, a year in, that you cannot move your own product to another team because the code was never really yours. Own it from day one, in writing.

    Web or mobile first?

    Follow the user, not the trend. If your users are clinicians working at a desk, build web first. If they are patients logging something on the move, or you need the phone camera or sensors, build mobile first. Most healthtech MVPs do not need both on day one, and building both doubles the cost and the compliance surface for no extra learning. Pick the one your core loop lives on and ship it. When you genuinely need the other platform, that is a custom software decision for phase two, funded by what you learned in phase one.

    After launch: measuring success and scaling up

    Launching the MVP is the start of the real work, not the end. Decide before launch what success looks like, and keep it to two or three numbers you actually care about. For most healthtech MVPs that is activation (did people complete the core loop even once), retention (did they come back), and one outcome signal tied to your promise, whether that is readings logged, reviews completed, or time saved. Vanity metrics like downloads tell you nothing about whether the product works.

    Then iterate from evidence, not opinion. The features you cut are not gone, they are waiting, and the MVP’s job is to tell you which of them earn their place. Scaling from an MVP to a full platform is mostly a sequence of these decisions: watch what real users do, add the next most valuable thing, keep the compliance foundations solid as you grow. The startups that scale well are the ones that treated the MVP as a question, not a smaller version of the answer.

    The mistakes we see most often

    • Building the full product and calling it an MVP.
    • Leaving compliance and security for “after launch,” then paying three to five times more to retrofit it.
    • Wiring up a third-party service without a BAA, the most common compliance failure there is.
    • No clinician in the room until the app is already built.
    • Two or three user types at launch when one would have proven the idea.
    • Hiring the cheapest team, discovering they do not know healthcare, and paying twice to fix it.
    • Custom-building auth, hosting, and infrastructure instead of using proven, BAA-eligible services.
    • Measuring downloads instead of whether anyone completes the core loop.

    Where to start with healthtech MVP development

    If you take one thing from all of this, make it this: write down your core loop in a single sentence with no “ands,” confirm which rules apply to it before you design anything, and build that loop properly. Everything else is roadmap. That one habit is the difference between a healthtech startup that learns fast and cheap and one that spends its whole seed round finding out it built the wrong thing.

    If you want a straight read on your specific product, scope, timeline, and what compliance will really take, a senior engineer who has shipped medical software will walk through it with you, no obligation. Book a discovery call.

    Frequently asked questions

    How much does it cost to build a healthcare MVP?

    In the US, an experienced agency usually builds a healthcare MVP for somewhere between $100,000 and $400,000, with the HIPAA work adding roughly 40 to 80 percent over a comparable consumer app. The exact number depends on how much patient data you handle, how many integrations you need, and how many user types you support at launch. Treat any figure before a scoping call as a rough range, and be wary of unusually low quotes, which usually mean the compliance work is missing from the plan.

    How long does it take to build a healthcare MVP?

    Three to six months is the honest range for a properly scoped first version. A quote of a few weeks almost always means the compliance and security work has been left out. The teams that ship at the short end cut scope hard and involved a clinician early.

    Does my healthcare MVP have to be HIPAA compliant?

    If it stores, processes, or transmits protected health information, then yes, and that shapes your architecture from day one. If it genuinely never touches identifiable health data, your obligations are lighter. Confirm which case you are in early, because assuming you are exempt when you are not is an expensive mistake to discover after launch.

    Does my health app need FDA clearance?

    Only if it functions as a medical device, meaning it is intended to diagnose, treat, cure, or prevent disease, or to affect the structure or function of the body. Many low-risk apps fall under the FDA’s enforcement discretion and do not need clearance, while higher-risk functions can require a 510(k) or premarket approval. Get a professional read before you build, because the answer changes your whole plan. This is not legal advice.

    Does my health app need FDA clearance?

    Only if it functions as a medical device, meaning it is intended to diagnose, treat, cure, or prevent disease, or to affect the structure or function of the body. Many low-risk apps fall under the FDA’s enforcement discretion and do not need clearance, while higher-risk functions can require a 510(k) or premarket approval. Get a professional read before you build, because the answer changes your whole plan. This is not legal advice.

    What features should a healthcare MVP include?

    Just the one core loop that proves your idea, built properly and compliantly, plus the security foundations underneath it. Everything else, the extra dashboards, roles, integrations, and languages, belongs on the roadmap. If your feature list has more than one “and,” you are describing a full product, not an MVP.

    Can a non-technical founder build a healthtech startup?

    Yes. You do not need to code to validate the idea, recruit and interview clinicians, and lead the product. You do need a technical partner or team you trust to build it compliantly, and you should own the code and IP. Validation and product leadership are exactly where non-technical founders add the most value.

    Should I build web or mobile first for a healthcare MVP?

    Follow your users. Clinicians at a desk means web first. Patients on the move, or a feature that needs the camera or sensors, means mobile first. Most MVPs need only one platform to prove the idea, and building both doubles the cost for no extra learning.

    What is the difference between an MVP and a prototype?

    A prototype is a clickable mockup with no real data, used to test an idea in days. An MVP is a working, compliant product with your one core feature, built to put in front of real users. A prototype answers “do people want this,” an MVP answers “does it work when it is real.”

    Should I use an in-house team, an agency, or freelancers?

    In-house makes sense once you have funding and a technical co-founder to lead it. Freelancers can handle a narrow piece but rarely own the whole compliant picture. For most early healthtech startups, a senior team that has shipped compliant health software before is the fastest safe route, because they have already made the expensive mistakes elsewhere.

    How do I protect my idea while building an MVP?

    Use an NDA with any team you talk to in depth, but put more weight on ownership: your contract should state plainly that you own the source code, IP, and documentation, with no license back to the agency. The real risk is not someone copying your idea, it is being unable to move your own product because the code was never truly yours.