Tag: EHR integration

  • AI Agents for Healthcare: Use Cases, Cost, and How to Build

    AI Agents for Healthcare: Use Cases, Cost, and How to Build

    AI agents for healthcare are software agents that take over the repetitive, admin-heavy work around care, booking appointments, handling intake, drafting clinical notes, chasing billing, so staff spend less time on paperwork and more on patients. The important part is what they are not: they are not a replacement for a clinician’s judgment, and they only belong in healthcare when they are built to protect patient data. That second point, compliance, is where most of the real work and most of the cost sits.

    If you have asked how. tobuild AI agents for healthcare and what it takes, this. guide is thestraight version. It covers what these agents actually do, how to build one step by step, what HIPAA compliance really means in practice, what it. costs in2026, and where a human has to stay in. the loop. Mobilionshas shipped healthcare software, including a privacy-first medical translation app, so this is from building the real thing, not a demo.

    Key takeaways

    • AI agents for healthcare are strongest at admin work: scheduling, intake, clinical notes, billing, and follow-up. Gartner expects agentic AI to cut administrative processing costs by up to 30 percent.
    • They do not diagnose or decide care on their own. A clinician stays in the loop for anything that touches a medical decision.
    • Compliance is the hard part. A healthcare agent must keep patient data (PHI) in HIPAA-eligible infrastructure, under a signed Business Associate Agreement, with encryption, audit logs, and minimum-necessary access.
    • Cost tracks compliance and integration more than the AI. A single-workflow agent runs about 35,000 to 70,000 dollars; a multi-location production system 70,000 to 150,000 and up.
    • The two biggest cost and time drivers are compliance engineering and connecting to your EHR and scheduling systems.

    What AI agents for healthcare actually do
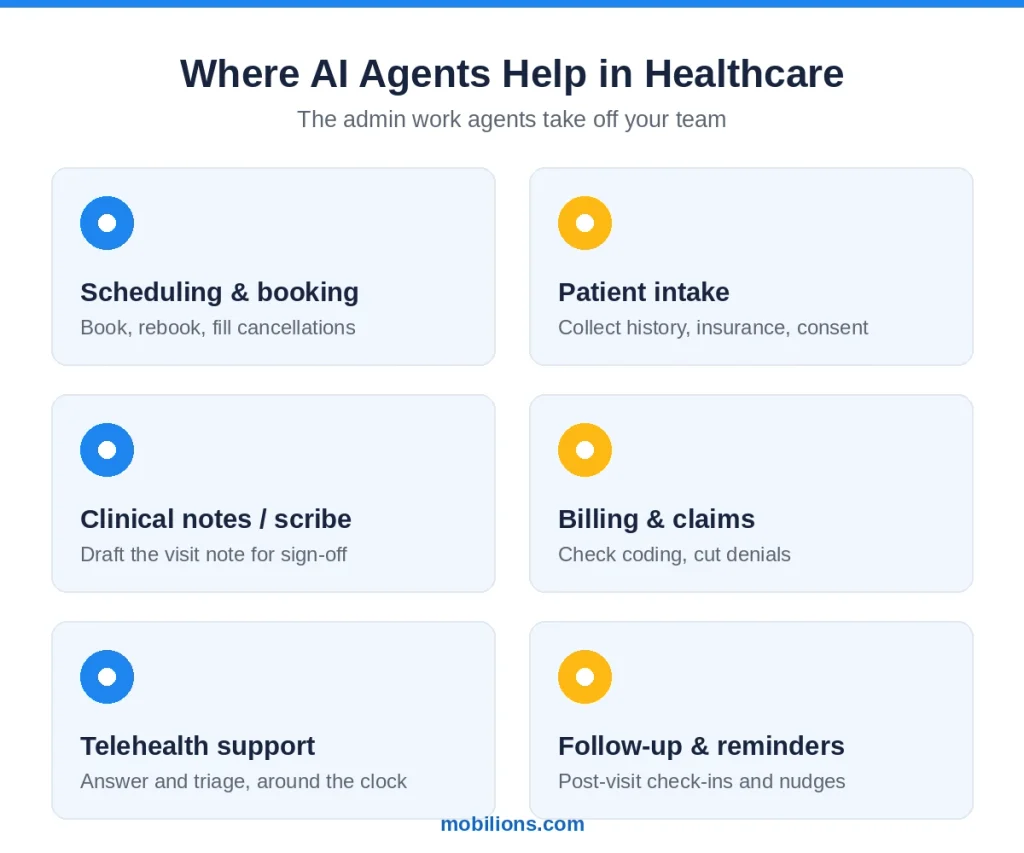
    AI agents for healthcare use cases: scheduling, patient intake, clinical scribing, billing, and follow-up.

    The clearest wins for AI agents for healthcare in 2026 are administrative, not clinical. These are the use cases moving from pilot to production across practices and hospital systems.

    • Patient scheduling and booking. Agents book, reschedule, and fill cancellations across your calendar, and cut phone-tag for the front desk.
    • Intake and onboarding. AI intake assistants collect history, insurance, and consent before the visit, so the first few minutes are care, not forms.
    • Clinical notes and scribing. Ambient AI scribes draft the visit note from the conversation, which the clinician reviews and signs. This is one of the biggest time-savers.
    • Billing and revenue cycle. Agents check coding, flag errors before claims go out, and chase the status of unpaid claims, reducing denials and manual follow-up.
    • Telehealth and patient support. Support agents answer common questions, triage messages, and route the ones that need a human, around the clock.
    • Follow-up and care coordination. Agents send reminders, check in after a visit, and coordinate multi-step admin across systems, with audit trails and human checkpoints.

    Notice the pattern: these free clinicians from paperwork rather than make medical calls. That is the line that keeps healthcare AI safe and useful, and it shapes everything in our AI agent development services for the sector.

    How to build an AI agent for healthcare, step by step

    How to build an AI agent for healthcare: workflow, guardrails, compliance, EHR integration, and human review.

    This is the part people really want when they ask how to build AI agents for healthcare. The order matters, because in healthcare compliance comes before code, not after.

    1. Scope one workflow and the outcome. Pick a single, high-pain task (scheduling, intake, or notes) and define what success looks like in hours saved or errors cut. Do not try to automate the whole practice at once.

    2. Lay the compliance foundation first. Decide where patient data will live (HIPAA-eligible infrastructure), get a Business Associate Agreement in place with every vendor that touches PHI, and set encryption, access control, and audit logging as the base, not an add-on.

    3. Connect to your EHR and systems. Integrate with your electronic health record and scheduling, usually over standards like HL7 and FHIR. This is the slow, unglamorous part, and the one that most often blows up naive timelines.

    4. Build the agent with guardrails. Wire the agent to its tools and data, add confidence thresholds, and make it ask for human approval on anything consequential. Retrieval keeps answers grounded in your real policies and records.

    5. Keep a clinician in the loop. Any output that touches a medical decision gets reviewed by a person. The agent drafts and proposes; the clinician decides and signs.

    6. Test, validate, deploy, and monitor. Evaluate the agent on real cases before launch, roll out to a small group first, and monitor accuracy and safety in production, because an agent that is quietly wrong is worse than none.

    HIPAA and compliance: what makes a healthcare AI agent legal

    A healthcare agent is only safe to use if it is compliant, and HIPAA is the baseline in the United States. Compliance is not a checkbox at the end; it is how the thing is built. In practice it means protected health information stays in HIPAA-eligible infrastructure, every vendor touching that data signs a Business Associate Agreement, data is encrypted in transit and at rest, access is minimum-necessary, and every action is logged for audit.

    One rule to carry into any vendor conversation: if a provider of AI agents for healthcare will not sign a BAA, walk away. That single question filters out most tools that are not actually built for healthcare. For the technical standards behind records exchange, HL7 FHIR is the common language your agent will speak to the EHR.

    How much do AI agents for healthcare cost in 2026?

    Cost tracks compliance and integration far more than the AI model. Here are the rough 2026 ranges.

    ScopeTypical 2026 costWhat you get
    Proof of concept8,000 to 20,000One workflow proven on sample data, no live PHI
    Single-workflow agent35,000 to 70,000Scheduling or intake for one practice, compliant and live
    Multi-workflow production70,000 to 150,000Multiple workflows, multi-location, full compliance tooling
    Enterprise / complex150,000 to 350,000+Hospital-scale, deep EHR integration, governance

    For AI agents for healthcare, the two biggest cost drivers are compliance engineering and EHR or scheduling integration, not the agent itself. Budget for running costs too: model usage, hosting in compliant infrastructure, and ongoing maintenance, usually 15 to 30 percent of the build per year. A small practice can still start: scope one workflow, prove it, and expand.

    Timeline: how long it takes

    For AI agents for healthcare, the build moves slower than other software, mostly because of compliance and EHR access. As a guide: a proof of concept in about 3 to 6 weeks, a single compliant workflow in 2 to 4 months, a multi-workflow production system in 4 to 8 months, and hospital-scale work in 8 to 12 months or more. The agent is rarely the bottleneck; data access, integration, and validation are.

    The risks, and where a human must stay

    For AI agents for healthcare, a balanced view means naming the limits. AI agents can be confidently wrong, so nothing that affects diagnosis, treatment, or a clinical decision should run without a clinician reviewing it. Accountability stays with the provider, not the software, which is exactly why human-in-the-loop is a design requirement in healthcare, not a nicety. Patient data carries real risk if mishandled, so security and consent are not optional. Used inside those lines, for admin and drafting with a person signing off, agents are safe and genuinely useful. Pushed past them, they are a liability.

    How to choose a healthcare AI partner

    When choosing a provider of AI agents for healthcare, look for a team that will sign a BAA without hesitation, has actually shipped healthcare software, designs compliance and human oversight in from the start, and is honest about what should stay with a clinician. Be wary of anyone who promises diagnosis-grade AI with no human in the loop, cannot explain where PHI lives, or treats HIPAA as paperwork to handle later.

    How Mobilions builds healthcare AI

    We build healthcare software the way the domain demands: compliance first, clinician in the loop, and honest about where an agent helps versus where it does not belong. We have shipped real healthcare products, including Careslate, a privacy-first medical translation app for real-time, two-way clinical conversations, so we build for the accuracy and data care the sector requires, not a generic chatbot.

    Mobilions has delivered software and AI since 2016, more than 250 projects for over 100 clients across 20-plus countries, and the same senior engineers scope, build, and support the system. See our healthcare software work and AI agent development services, or book a discovery call to talk through one workflow.

    Frequently asked questions

    What are AI agents for healthcare?

    AI agents for healthcare are software agents that handle admin-heavy tasks around care, such as scheduling, patient intake, clinical note drafting, billing, and follow-up. They act across your systems with guardrails and human oversight. They support staff and clinicians; they do not replace clinical judgment.

    Will AI replace doctors?

    No. The strong, safe use of AI in healthcare is administrative and supportive, not diagnostic. Agents take paperwork and routine tasks off clinicians so they spend more time with patients. Any output touching a medical decision is reviewed and signed by a clinician, who remains accountable.

    Are AI agents for healthcare HIPAA compliant?

    They can be, when built correctly. That means protected health information stays in HIPAA-eligible infrastructure, every vendor touching it signs a Business Associate Agreement, data is encrypted, access is minimum-necessary, and actions are logged. If a vendor will not sign a BAA, the tool is not safe for healthcare.

    How much does a healthcare AI agent cost in 2026?

    A proof of concept runs about 8,000 to 20,000 dollars, a single compliant workflow 35,000 to 70,000, and a multi-location production system 70,000 to 150,000, with enterprise builds higher. Compliance engineering and EHR integration are the main cost drivers, not the AI model.

    How long does it take to build one?

    Roughly 3 to 6 weeks for a proof of concept, 2 to 4 months for a single compliant workflow, and 4 to 8 months for a multi-workflow production system. Healthcare is slower than other software because of compliance and EHR access, not the agent itself.

    Do AI agents connect to our EHR?

    Yes, that is central to the build. Agents integrate with your electronic health record and scheduling systems, usually over standards like HL7 and FHIR. This integration is the slow, important part of the project and a major driver of cost and timeline.

    How do AI agents protect patient data?

    Through HIPAA-eligible infrastructure, a signed Business Associate Agreement, encryption in transit and at rest, minimum-necessary access, and full audit logging. For regulated data, security and consent are designed in from the start, and sensitive actions require human approval.

    Can small practices afford AI agents?

    Yes, by starting small. Scope one high-pain workflow, such as scheduling or intake, prove it saves time, and expand from there. You do not need a hospital budget; you need focus on the task that costs your team the most hours.

    What tasks can AI agents automate in a medical practice?

    Scheduling and rebooking, patient intake and consent, drafting clinical notes from visits, billing and claim checks, answering routine patient questions, appointment reminders, and post-visit follow-up. The common thread is repetitive admin work, not clinical decisions.

    What happens if the AI gets something wrong?

    That is why healthcare agents keep a human in the loop. The agent drafts or proposes; a clinician reviews and decides on anything clinical, and accountability stays with the provider. Good builds also add confidence thresholds, evaluation, and monitoring to catch errors before they reach a patient.

  • Healthcare Mobile App Development: A Complete 2026 Guide

    Healthcare Mobile App Development: A Complete 2026 Guide

    Healthcare mobile app development is the process of building iOS or Android apps that handle patient or clinical data, which means HIPAA compliance, strong security, and often EHR integration are part of the job from day one, not features you bolt on later. A basic HIPAA-ready MVP typically starts around $60,000 and ships in about four to six months. The cost and timeline track compliance, the integrations you need, and whether your app is a wellness tool or a regulated medical device.

    Most healthcare apps do not fail because the idea was wrong. They fail because the team treated a medical app like a regular app, and then hit compliance, security, and integration walls halfway through the build. By then the budget is spent and the timeline is gone.

    This guide is written to keep you out of that hole. It covers what healthcare mobile app development actually involves in 2026, what it costs, how long it takes, where HIPAA and the FDA fit in, and how to choose a team that has shipped this kind of app before. We have built and shipped mobile health products since 2016, including medical translation and nutrition platforms where a wrong answer carries real consequences, so the advice here is what we would tell a founder over a call.

    Key takeaways

    • Healthcare app development means compliance and security are part of the build from day one, not add-ons.
    • Know early whether your app is a wellness product or an FDA-regulated medical device. The line is narrower than most founders expect.
    • HIPAA in practice means AES-256 at rest, TLS 1.2 or higher in transit, MFA, audit logs, and signed BAAs with every vendor.
    • A HIPAA-ready MVP starts around $60,000 and ships in four to six months. EHR integration adds the most to both cost and timeline.
    • Choose a team with shipped healthcare apps, compliance fluency, named senior engineers, and clear code ownership.

    What healthcare mobile app development actually means

    A healthcare app is any mobile app that touches health data or clinical workflows. That covers a lot of ground: a patient booking a telehealth visit, a nurse checking a chart at the bedside, someone logging blood sugar, a therapist running a session. What ties them together is the data. The moment your app stores, moves, or displays information that can identify a person and their health, you are in regulated territory, and the rules shape every decision after that.

    This is the part founders underestimate. In a normal app, security and privacy are good practice. In a healthcare app, they are the product. Encryption, access control, audit logs, and consent are not features you add if there is time. They are the foundation the rest of the app sits on.

    Health app vs medical app: the line that changes everything

    Not every health app is a medical device, and the difference decides how heavy your build is. A wellness app that tracks steps, logs meals, or reminds you to take medication is usually a general wellness product with a lighter regulatory load. An app that diagnoses, treats, or drives a clinical decision can be a medical device that the FDA regulates as Software as a Medical Device (SaMD).

    The FDA draws the line at intended use. A blood pressure app that just displays your readings usually sits in enforcement discretion. Add a feature that interprets those readings and says you may have hypertension and should ask about medication, and you have crossed into regulated territory.

    That distinction is set out in the FDA’s guidance on device software functions and mobile medical applications. Check the current version before you finalise your feature list, because the boundary has moved more than once and it moves in the direction of more scrutiny, not less. Decide which side you are on before you build. It changes your timeline, your budget, and your legal exposure.

    HIPAA compliance: what it really requires

    If your app handles protected health information for anyone in the US, HIPAA applies. It is not a certificate you buy or a checkbox at the end. It is a set of safeguards baked into how the app is built, hosted, and run. Here is what that means in practice.

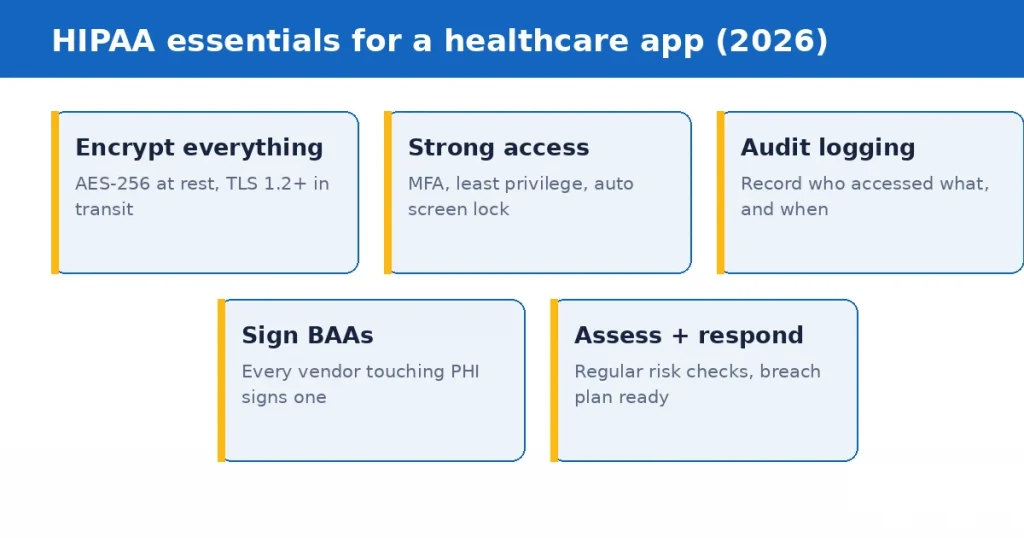
    • Encryption everywhere. Protected health information must be encrypted at rest and in transit. The working standard is AES-256 for stored data and TLS 1.2 or higher for data moving across the network.
    • Strong access control. Every user gets the minimum access they need, with multi-factor authentication, automatic screen lock, and session timeouts. On mobile specifically, that includes blocking screenshots on iOS and screen recording on Android so health data does not leak out the side door.
    • Audit logging. The system records who accessed what and when, so a breach can be investigated and access can be proven.
    • A Business Associate Agreement (BAA). Every vendor that touches the data, your cloud host, your video provider, your analytics, must sign a BAA. Using a service that will not sign one is a compliance gap by itself.
    • Risk assessments and breach response. HIPAA expects regular security risk assessments and a real plan for breach notification.
    Five HIPAA essentials for a healthcare app: encryption, access control, audit logging, business associate agreements, and risk assessment

    The Security Rule has been under active revision, and the direction of travel is toward making encryption and multi-factor authentication mandatory rather than addressable, with tighter breach timelines. Build to the stricter bar now. It is cheaper than retrofitting when a rule finalises, and none of it is wasted work even if the timeline slips.

    Founder note

    HIPAA compliance is not the whole app, it is a property of the app. It adds meaningfully to the base build cost, but retrofitting it into a non-compliant app later costs far more and sometimes means rebuilding. Start compliant.

    iOS vs Android: which platform first

    You do not have to pick one forever, but for an MVP, building one platform well beats building two platforms poorly. The right first choice depends on who your users are.

    If your users are patients in the US, iOS often makes sense first, since iPhone holds a large share of the US consumer market and Apple’s health frameworks are mature. If your app is for clinicians or serves a broad or global population, Android may matter more because of device range. If your budget is tight and you want both from day one, cross-platform is the practical answer, which brings us to the next decision.

    Native or cross-platform

    Cross-platform frameworks like Flutter and React Native let you build one codebase for both iOS and Android, which lowers cost and speeds up delivery. For most healthcare apps, that is the right call.

    You reach for native when you need heavy device-specific performance, deep integration with Apple HealthKit or Google Health Connect, or tight control over hardware like Bluetooth medical devices. Continuous glucose monitors, connected inhalers, and anything with a real-time data stream from a device tend to push you native, or at least native for that one module.

    A good team helps you decide based on your product, not on what they prefer to build. If a team recommends the same stack for every client regardless of the brief, that tells you something.

    We work across Flutter app development and React Native app development as well as native iOS and Android, and the choice genuinely changes per project.

    Core features of a healthcare app

    The exact feature set depends on whether your app is patient-facing, provider-facing, or both. These are the building blocks most healthcare apps draw from.

    • Secure sign-in and identity: MFA, biometric login, role-based access.
    • Patient profiles and health records, with consent controls.
    • Appointment booking and reminders.
    • Telehealth: encrypted video, chat, and file sharing.
    • Tracking and monitoring: medication, symptoms, vitals, often synced from wearables.
    • Notifications that respect privacy, with no health details on a lock screen.
    • EHR integration, so the app talks to the systems clinicians already use.

    The trap is trying to ship all of this at once. The apps that succeed launch with the two or three features that solve the core problem, prove people use them, and add the rest based on real feedback.

    What to cut from version one

    This is the conversation we have with almost every healthcare founder, and it saves more money than any other decision in the project.

    Cut multi-role from the first release. Building for patients and clinicians and administrators at once triples your permission model, your testing surface, and your compliance review. Pick the role that proves the product and build only for them.

    Cut EHR integration if you can prove value without it. It is the single biggest cost and schedule driver. Plenty of products validate with manual data entry or a simple export first, then integrate once a health system has actually committed.

    Cut native wearable integration. Apple HealthKit and Google Health Connect sound cheap because the SDKs are free. The cost is in the edge cases: missing data, duplicate readings, timezone drift, and users who revoke permission halfway through a study. Add it when the core loop works.

    Cut offline mode unless clinicians in the field are your users. Offline-first is a genuine engineering commitment involving conflict resolution and sync logic. It is worth it for a community health worker in a low-connectivity area. It is not worth it for an urban telehealth app.

    Do not cut audit logging, access control, or encryption. These are the things founders try to defer and they are the things you cannot add cleanly later. Every retrofit we have done started as a deferral.

    The pattern across the healthcare products we have shipped is the same: the launch feature set is smaller than the founder first imagined, and the compliance foundation is deeper. That combination ships. The reverse does not.

    EHR integration: the part that quietly drives cost

    If your app needs to read or write clinical data, it has to connect to electronic health record systems like Epic or Cerner. This is where a lot of healthcare budgets get their surprise.

    Modern EHRs expose FHIR-compliant APIs, the current healthcare data standard, which makes standard integrations relatively clean. Older systems that rely on HL7 v2 messaging or custom interface engines are a heavier lift.

    Three things drive the difference in effort:

    Which standard the system speaks. A FHIR API with good documentation is a different project from an HL7 v2 feed arriving over a legacy interface engine.

    Read or write. Reading patient data is far simpler than writing back into a clinical record. Write-back triggers a much heavier review process on the health system’s side, and their timeline is not yours to control.

    Whose sandbox you get. Some health systems have a working developer sandbox and a defined app review process. Others have a committee and a six-week wait for a call. This is often the real schedule risk and it has nothing to do with your code.

    If EHR integration is in your plan, scope it early and start the conversation with the health system before you start building. Budget and schedule both move more on this than on almost anything else.

    How much does healthcare app development cost in 2026

    There is no single price, because a wellness tracker and a telemedicine platform with EHR write-back are completely different products. The ranges below reflect what we see when scoping healthcare builds for the US market. Treat them as a starting frame, not a quote. We scope your specific app before giving a real number.

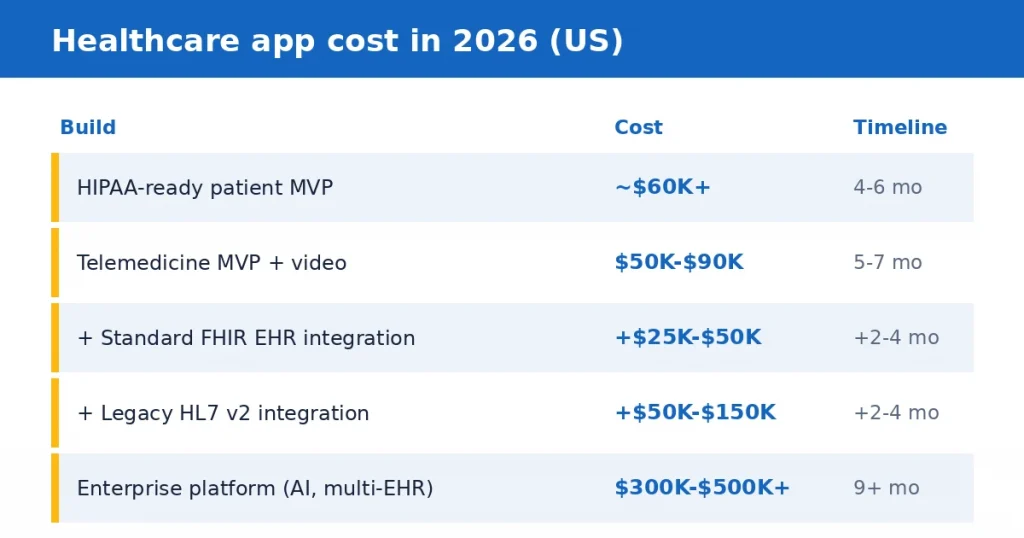
    App typeTypical cost (US, 2026)Rough timeline
    HIPAA-ready patient MVPAround $60,000 and up4 to 6 months
    Telemedicine MVP (portals, encrypted video, booking)$50,000 to $90,0005 to 7 months
    Real-time video infrastructure (add-on)$15,000 to $40,000Included above
    Standard FHIR EHR integrationAdd $25,000 to $50,000Add 2 to 4 months
    Legacy HL7 v2 integrationAdd $50,000 to $150,000Add 2 to 4 months
    Enterprise platform (AI, multi-EHR, multi-platform)$300,000 to $500,000 and up9 months and up
    Healthcare app development cost and timeline ranges in 2026, from a HIPAA-ready MVP at around 60,000 dollars to an enterprise platform above 300,000 dollars

    Compliance work is not a line item you can remove. It runs through security engineering, documentation, audit logging, vendor agreements, and testing, and it is a meaningful share of any healthcare build.

    Why healthcare apps cost more than regular apps

    The extra cost is not padding. It buys encryption and security engineering, compliance work and documentation, audit logging, signed vendor agreements, careful testing against real clinical workflows, and integrations that have to be exact because a wrong record is a patient safety issue.

    A consumer photo app can ship a bug and patch it Tuesday. A medication app cannot.

    How long does it take

    A focused HIPAA-ready MVP usually ships in about four to six months. Add telehealth video and you are closer to five to seven. Add EHR integration and you add two to four months on top.

    The timeline is driven less by screen count and more by compliance, integrations, and testing. There is also a category of delay that is not yours to control: health system review cycles, app store review for medical claims, and legal sign-off on your privacy policy and consent flows. Build slack for those into the plan rather than discovering them in month five.

    How to choose a healthcare app development company

    This is a specialist build, and general app teams get healthcare wrong in expensive ways. Here is how to tell a team that has shipped medical apps from one that will learn on your budget.

    • Shipped healthcare work. Ask for live health apps they have built, ideally in your space. Compliance experience shows up in the details they mention without being asked.
    • Compliance fluency. They should talk about HIPAA, BAAs, encryption, and the health app versus medical device line naturally, and tell you early if you are heading toward FDA territory.
    • Named senior engineers. You want senior people on your project, not a pitch team that hands the build to juniors. Ask who writes your code and whether you can interview them.
    • Clear ownership. In writing, you own the source code, the IP, and the app store listings, with no lock-in.
    • A real post-launch plan. Healthcare apps need ongoing maintenance, security patching, and OS updates. A team with no answer for month twelve is planning to disappear.

    Questions worth asking on the first call

    Five questions that separate teams quickly:

    1. Which of your healthcare apps is live right now, and can I download it?
    2. Who signs the BAA, you or the client, and which vendors in your usual stack will sign one?
    3. Based on what I have described, do you think this is a medical device? Why?
    4. What would you cut from my first version, and what would you refuse to cut?
    5. Who exactly writes the code, and can I speak to them before we sign?

    A team that has done this work answers all five without hedging. A team that has not will be vague on two or three, usually the medical device question and the one about who writes the code.

    Red flags to walk away from

    • A quote far below everyone else, which usually means compliance is missing from the scope.
    • Vague answers on HIPAA, or a promise that compliance is easy.
    • No named engineers and no shipped healthcare apps to show.
    • Fuzzy code-ownership terms.

    If you are weighing an in-house hire against an agency, our hire mobile developers page covers the engagement models, enterprise mobile app and the honest answer is that healthcare is one of the areas where prior domain experience matters more than raw headcount.

    How we approach healthcare apps at Mobilions

    We build healthcare apps compliant from the first commit, not compliant-later. That means encryption, access control, and audit logging in the foundation, signed BAAs with every vendor in the stack, and an honest early read on whether your app is a wellness product or heading toward SaMD. Senior engineers scope, build, and support the product, and you own the code, the IP, and the documentation throughout.

    We have shipped mobile health products since 2016. Careslate is a HIPAA-compliant AI medical translation app with live two-way audio built on a custom three-stage pipeline, used in clinical settings where a mistranslation has consequences. JoinBeet is a personalised medical nutrition platform with meal matching, wearable sync, and role-based admin access.

    Both are on our healthcare software development page alongside how we approach the sector, and the mobile side of that work sits under mobile app development.

    Ready to scope your healthcare app?

    Tell us what you want to build and who it is for. A senior engineer will give you an honest read on cost, timeline, and the compliance path, including the parts you can cut from the first version. Book a discovery call.

    Frequently asked questions

    How much does it cost to build a healthcare app?

    In the US in 2026, a HIPAA-ready patient MVP typically starts around $60,000, a telemedicine MVP runs $50,000 to $90,000, and enterprise platforms with AI and EHR integration reach $300,000 to $500,000 or more. The number tracks scope, integrations, and whether the app is regulated. Compliance work is a meaningful share of any healthcare build and cannot be removed from the scope.

    How long does it take to develop a healthcare app?

    A focused HIPAA-ready MVP usually ships in about four to six months. Telehealth video pushes that to five to seven months, and EHR integration adds another two to four months. Compliance and testing drive the timeline more than the number of screens, and health system review cycles can add delay you do not control.

    What is HIPAA compliance for a mobile app?

    It is a set of safeguards for protected health information: AES-256 encryption at rest, TLS 1.2 or higher in transit, multi-factor authentication, access controls, audit logging, and signed Business Associate Agreements with every vendor that touches the data. It is built into the app, not added at the end.

    Does my healthcare app need FDA approval?

    Only if it functions as a medical device, meaning it diagnoses, treats, or drives a clinical decision. Wellness trackers and appointment apps usually do not. Apps that interpret data and make clinical claims can be regulated as Software as a Medical Device. The line is narrow, so get an assessment early rather than after the build.

    What is the difference between a health app and a medical app?

    A health or wellness app tracks or supports general wellbeing, like steps, meals, or reminders, with a lighter regulatory load. A medical app diagnoses, treats, or informs a clinical decision and can be an FDA-regulated medical device. Intended use decides which one you are building, not the feature list on its own.

    Should I build for iOS or Android first?

    If your users are US patients, iOS is often a strong first choice. If you serve clinicians or a broad or global audience, Android may matter more. If you want both on a tight budget, a cross-platform build with Flutter or React Native is usually the practical answer.

    How much does HIPAA compliance add to the cost?

    It is not a separate line you can price and remove. Compliance runs through security engineering, audit logging, documentation, vendor agreements, and testing, so it raises the cost of the whole build rather than sitting beside it. Retrofitting compliance into an app built without it costs far more, so it is cheaper to start compliant.

    What is EHR integration and why does it cost so much?

    EHR integration connects your app to systems like Epic or Cerner so it can read or write clinical data. A modern FHIR integration commonly adds $25,000 to $50,000, while legacy HL7 v2 integration can add $50,000 to $150,000 and two to four months. Writing back into a clinical record is significantly harder than reading, and health system review timelines are not yours to control.

    Can I build a healthcare app without technical skills?

    Yes, most healthcare app founders are not engineers. You bring the clinical or business insight and partner with a team that handles the build and compliance. What matters is choosing a team that has shipped healthcare apps and can guide you through HIPAA and the medical device question.

    What features should my healthcare app include?

    Start with secure sign-in, patient profiles with consent, and the two or three features that solve your core problem, whether that is booking, telehealth video, or tracking. Add EHR integration, wearables, and extra features later based on real user feedback, not all at once.

    How do I make sure my healthcare app is secure?

    Encrypt data at rest and in transit, enforce MFA and least-privilege access, log every access, block screenshots and screen recording of health data, sign BAAs with all vendors, run regular security risk assessments, and test against real clinical workflows before launch.

    Does Mobilions build healthcare apps?

    Yes. We build HIPAA-compliant iOS, Android, and cross-platform healthcare apps, and have shipped mobile health products since 2016, including a medical translation app for clinical settings and a nutrition platform with wearable sync. We build compliant from day one and hand you full ownership of the code and IP.